Cardiogenic Shock
Definition
A cardiac disorder that produces both clinical and biochemical evidence of sustained tissue hypoperfusion, irrespective of blood pressure. There is no specific blood-pressure threshold; lactate >2 mmol/L supplies the biochemical evidence of hypoperfusion. Cardiogenic shock is one of the most common causes of admission to contemporary cardiac intensive care units, carrying 30%–40% short-term mortality and approximately 50% at one year. (sources/cardiogenic-shock-acc-2025, rating: very high)
This page covers the condition and its management. Decompensated heart failure without shock — decompensated left- and right-sided failure and acute pulmonary oedema — is on concepts/Decompensated-HF-Management; device mechanics are on concepts/IABP, concepts/ECPELLA and concepts/Pulmonary-Artery-Pulsatility-Index; individual trials have their own entity pages.
Key Concepts
Epidemiology
- Short-term in-hospital mortality 30%–40%; 1-year mortality approaching or exceeding 50%. (sources/cardiogenic-shock-acc-2025, rating: very high)
- In-hospital mortality of AMI-related shock (Killip IV) fell from 62.2% in 1997 to 36.3% in 2017 in the Swiss AMI registry; the Tokyo CCU Network recorded a parallel fall from 38.5% to 27.2% between 2007 and 2016. (sources/mcs-jic-2023, rating: high)
- Non-infarction causes now outnumber AMI-related shock in contemporary registries — an epidemiological shift attributable to improved MI prevention and revascularisation. (sources/cardiogenic-shock-nejm-2026, rating: very high)
- Mortality by aetiology (SHARC registry; n=8,974): mixed shock 48% > AMI-related 41% > new heart-failure-related 31% = secondary 31% > acute-on-chronic heart-failure-related 25%.
- 71% of patients with AMI-related shock are frail — a major prognostic factor and a central consideration in device decisions.
- Cause of death, in descending order: persistent shock, arrhythmia, anoxic brain injury, respiratory failure.
- Japanese DPC database (n=160,559; 2010–2020): IABP-alone use fell from 80.5% to 65.3%, Impella rose from 0% to 5.0%, and ECMO from 19.5% to 29.6% — the device landscape shifting toward more powerful support. (sources/mcs-jic-2023)
Phenotypes and Aetiology — the SARC Classification
The Shock Academic Research Consortium divides shock by cause rather than by device, because cause predicts outcome more strongly than haemodynamics:
- AMI-related shock: shock from acute MI — LV, RV or biventricular dysfunction, mechanical complications of MI, arrhythmias or advanced heart block in the setting of MI.
- Heart-failure-related shock: primary myocardial dysfunction, ischaemic or non-ischaemic; subdivided into de novo and acute-on-chronic, with myocarditis, Takotsubo, peripartum cardiomyopathy, tachycardia-related cardiomyopathy, HCM, amyloidosis and sarcoidosis among the subtypes.
- Post-cardiotomy shock: after cardiac surgery.
- Secondary shock: arrhythmia, valvular disease, pericardial disease, other causes.
- Mixed shock: cardiogenic shock with at least one additional concurrent cause (septic, hypovolaemic); highest mortality at 48%. (sources/cardiogenic-shock-nejm-2026, rating: very high)
- Post-cardiac-arrest phenotype: myocardial stunning after return of spontaneous circulation. High lactate from the no-flow interval does not correlate with cardiac index, and 20%–30% die of brain injury rather than circulatory failure.
- Ventricular involvement: the right ventricle is involved in 44% of AMI-related shock and more often in non-AMI shock; a biventricular profile carries an adverse prognosis.
Early Recognition — SUSPECT CS
Diagnosis does not require invasive haemodynamics; clinical, laboratory and imaging data suffice.
| Letter | Domain | Threshold |
|---|---|---|
| S | Symptoms and signs | Altered mental status, cold/clammy extremities, pulse pressure <25% of systolic, raised JVP, crackles, orthopnoea |
| U | Urine output | <30 mL/h (<0.5 mL/kg·h) |
| S | Sustained hypotension | SBP <90 or MAP <65 mmHg for >30 min, a fall of >30 mmHg from baseline, or support needed to maintain pressure |
| P | Perfusion | Lactate >2 mmol/L; ALT >200 U/L; creatinine ≥2× ULN; pH <7.2 |
| E | ECG and echocardiogram | Acute ischaemia, STEMI, wall-motion abnormality, LV/RV dysfunction, valvular pathology |
| C | Congestion | Physical or haemodynamic evidence; LV versus RV versus biventricular |
| T | Triage | Shock-team activation or transfer |
(sources/cardiogenic-shock-acc-2025, rating: very high)
Normotensive shock — end-organ hypoperfusion without hypotension — carries increased mortality and is the presentation most easily missed.
Severity — The SCAI Stages
The Society for Cardiovascular Angiography and Interventions system classifies severity from "at risk" to "extremis" on clinical, haemodynamic and biochemical grounds. The ACC 2025 guidance endorses it as the standard severity tool. (sources/cardiogenic-shock-acc-2025, rating: very high; sources/cardiogenic-shock-nejm-2026)
| Stage | Features |
|---|---|
| A — At risk | No signs of shock, but at risk (large MI, HF exacerbation); normal haemodynamics; lactate ≤2 mmol/L |
| B — Beginning | Relative hypotension or tachycardia without hypoperfusion; filling pressures may be elevated; lactate ≤2 mmol/L |
| C — Classic | Hypoperfusion requiring intervention; lactate >2 mmol/L; CI <2.2 L/min/m²; PCWP >15 mmHg |
| D — Deteriorating | Rising or persistently elevated lactate; escalating pressors or addition of MCS; deterioration despite support |
| E — Extremis | Lactate >8 mmol/L; profound hypotension despite maximal support; often cardiac arrest or CPR |
Right heart catheterisation values map onto the stages:
| Phenotype | RAP | PAWP | CI (L/min/m²) | MAP | SVRi | Profile | Lactate |
|---|---|---|---|---|---|---|---|
| A — At risk | ≤10 mmHg | ≤15 mmHg | ≥2.5 | ≥60 mmHg | normal | warm and dry | normal |
| B — Beginning | >10 mmHg | >15 mmHg | ≥2.5 | ≥60 mmHg | normal | warm and wet | normal |
| C — Classic | >10 mmHg | >15 mmHg | <2.5 | <60 mmHg | increased | cold and wet | ≥2 mmol/L |
| D — Deteriorating | >10 mmHg | >15 mmHg | <2.2 | <60 mmHg | decreased | cold and wet | ≥2 mmol/L |
| E — Extremis | >10 mmHg | >20 mmHg | <1.8 | <60 mmHg | decreased | cold and wet | ≥8 mmol/L |
(sources/rhc-hf-ehj-2025, rating: high)
- What separates C from D is not filling pressure but SVRi and CI. SVRi is increased in Stage C from compensatory vasoconstriction and decreased in Stage D as that reserve is lost, with CI falling from <2.5 to <2.2 L/min/m². Stage E is separated by PAWP >20 mmHg, CI <1.8 L/min/m² and lactate ≥8 mmol/L.
- RAP >10 mmHg and PAWP >15 mmHg are common to Stages B–E; RAP is not what distinguishes them.
The framework also discriminates the two important mimics, which SCAI staging alone does not: (sources/rhc-hf-ehj-2025)
| Phenotype | PAWP | CI (L/min/m²) | SVRi | Profile |
|---|---|---|---|---|
| Vasodilatory (septic, allergic) | ≤15 mmHg | ≥2.5 | decreased | warm and dry |
| Mixed shock | >15 mmHg | <2.2 or ≥2.2 | decreased or normal | warm or cold and wet |
| Isolated right ventricular | <18 mmHg (RAP:PAWP ≥0.8) | <2.2 | increased | RAP >14 mmHg; RVSWI low |
- Vasodilatory shock is the key discriminator from Stage C: high CI with a normal PAWP and low SVRi, against low CI, high PAWP and high SVRi in classic cardiogenic shock.
- Isolated RV shock mimics cardiogenic shock clinically but not haemodynamically — PAWP normal-to-low with markedly elevated RAP and RAP:PAWP ≥0.8 — so any staging that looks only at CI and PAWP will miss it.
- Mixed shock spans the boundary, with elevated PAWP and reduced SVRi: the combination identifying patients who need vasopressor and inotrope or mechanical support simultaneously.
Prognosis is stepwise and trajectory-dependent:
- In-hospital mortality by stage (Jentzer et al.; n=10,004; Mayo Clinic CICU 2007–2015): A 3.0%, B 7.1%, C 12.4%, D 40.4%, E 67.0%. (sources/mcs-jic-2023, rating: high)
- Stage B is the critical intervention window — the highest risk of worsening within 24 hours of diagnosis — and most patients change stage within that period, so serial reassessment is essential. (sources/cardiogenic-shock-acc-2025, rating: very high)
- Trajectory predicts outcome independently of admission stage (Hanson et al.; n=300 AMI-related shock; NCSI registry): Stage C at admission surviving as C at 24 h — 84% survival; C worsening to D — 55%; C worsening to E — 17%. (sources/mcs-jic-2023)
Systems of Care and the Shock Team
- Level 1 centres hold full 24/7 expertise, full temporary MCS capability, and durable LVAD plus transplant; Level 2 hold intermediate capability and some temporary MCS; Level 3 are community hospitals with basic cardiovascular care only. (sources/cardiogenic-shock-acc-2025, rating: very high)
- AMI-related shock refractory to revascularisation is almost always transferred to a Level 1 centre. Any vasoactive agent, consideration of temporary MCS, or cardiac arrest should prompt immediate contact with the regional Level 1 centre — "it is never too early to contact the CS regional center."
- High-volume centres (≥107 shock cases per year) are associated with improved outcomes in observational data. (sources/cardiogenic-shock-aha-2017, rating: high)
- Shock-team activation — critical care cardiology, advanced HF/transplant, interventional cardiology, cardiac surgery, with ECMO/perfusion and palliative care as needed — is associated with lower risk-adjusted CICU mortality.
- Mobile ECMO teams are an emerging strategy for high-acuity interhospital transfer.
Invasive Haemodynamic Monitoring
- Cardiac power output is the single strongest haemodynamic predictor of mortality in shock (SHOCK trial registry), superior to CI or MAP alone. CPO (watts) = (MAP × CO) / 451. (sources/mcs-ehj-2014, rating: medium; sources/mcs-jic-2023, rating: high)
- CPO/lactate decision rule at 12–24 h: CPO <0.6 W with lactate >4 mmol/L → escalate to device support; CPO >0.6 W with lactate <4 mmol/L → consider weaning catecholamines and temporary MCS.
- Beyond 24 hours, haemodynamic indices lose their prognostic primacy: MODS severity (APACHE II, SAPS II) and SIRS biomarkers (IL-6, RAGE) predict mortality more accurately, and CI alone is unrelated to survival beyond 24 h in AMI-related shock.
- PAC use is associated with improved outcomes in retrospective and registry data; there is no shock-specific RCT (PACCS ongoing), and the ESCAPE trial is inapplicable because it enrolled decompensated HF rather than shock. Complete haemodynamic profiling, versus incomplete or none, is associated with lower in-hospital mortality; early assessment within 12 hours is associated with improved outcomes. (sources/cardiogenic-shock-acc-2025, rating: very high)
- Congestion profiles: LV-dominant (PCWP >15 mmHg with normal or low RA pressure), RV-dominant (RA pressure >15 mmHg, RA/PCWP ratio >0.63–0.86, near-normal PCWP), and biventricular (both elevated, adverse prognosis, more common in non-AMI shock).
- Recovery markers: reappearance of pulse pressure under VA-ECMO is a prerequisite before weaning; a rising LVOT-VTI on echocardiography during Impella weaning; ETCO₂ as an emerging non-invasive metric; and the Impella pulsatility index, whose rise indicates returning native contraction.
- HF-related shock is systematically under-triaged. AMI-related shock deteriorates abruptly with early, clinically apparent hypoperfusion; HF-related shock shows insidious low output with chronic adaptation, so haemodynamic derangement is often more severe while end-organ function is preserved and lactate is normal at presentation. Right heart catheterisation unmasks the severity. Targets: RAP 8–12 mmHg, PCWP ≤15 mmHg, CI ≥2.2 L/min/m². (sources/rhc-hf-jacchf-2024, rating: high)
Vasopressors and Inotropes
No vasoactive agent has demonstrated a mortality benefit in shock. Use the lowest dose for the shortest duration, and address congestion in parallel: IV loop diuretics → thiazide augmentation → ultrafiltration or renal replacement. (sources/cardiogenic-shock-acc-2025, rating: very high)
| Agent | Class | Key data | Caution |
|---|---|---|---|
| Norepinephrine | Vasopressor | First-line; balanced alpha/beta activity | — |
| Dopamine | Vasopressor/inotrope | More arrhythmic events vs norepinephrine (n=1,679); no mortality difference | Avoid as first-line |
| Epinephrine | Vasopressor/inotrope | Similar cardiac index to norepinephrine but worse heart rate and lactic acidosis | Metabolic confound |
| Phenylephrine | Pure vasopressor | Reflex bradycardia reduces cardiac output | Strongly discouraged as first-line |
| Dobutamine | Inotrope | Equivalent to milrinone (DOREMI) | Tachyarrhythmia |
| Milrinone | Inodilator | Equivalent to dobutamine (DOREMI) | Renally cleared, long half-life — caution with worsening renal function |
| Levosimendan | Calcium sensitiser / inodilator | Failed a dedicated VA-ECMO weaning RCT; the only inotrope with zero myocardial oxygen cost | Monotherapy only if SBP >90 mmHg |
- Goal MAP >60–65 mmHg. An RCT testing 55 versus 65 mmHg is ongoing; the lower target may reduce LV afterload but risks organ hypoperfusion. (sources/cardiogenic-shock-nejm-2026, rating: very high)
- Pure vasopressors as first-line are strongly discouraged — reflex bradycardia reduces cardiac output and worsens tissue perfusion.
- Inodilators and vasodilators are for normotensive shock with elevated SVR; under ECPELLA, adding a vasodilator reduces pressure-volume area and increases total system flow.
- β-blockers and RAAS inhibitors must not be initiated or continued in active shock. Resume only after haemodynamic stability for ≥24 hours off all vasopressors and inotropes. (sources/cardiogenic-shock-aha-2017, rating: high)
- Fluids only where hypovolaemia exists without congestion and a passive leg-raise test is positive; tailor to LV-dominant versus RV-dominant failure.
- Mechanism, dosing and trial detail for levosimendan — including its PPCM, Takotsubo and cardiac-surgery indications and its conflicting arrhythmia signal — are on entities/Levosimendan.
Revascularisation in AMI-CS
- Early revascularisation showed no 30-day benefit in SHOCK but reduced mortality up to 6 years, and is strongly recommended. (sources/cardiogenic-shock-nejm-2026, rating: very high)
- 70%–80% have multivessel disease. CULPRIT-SHOCK compared culprit-only PCI (45.9%) with immediate multivessel PCI (55.4%) on death or renal replacement therapy (RR 0.83; P=0.01), driven by mortality: culprit-only PCI is the standard, with staged revascularisation after stabilisation in most survivors.
- A pharmacoinvasive approach may benefit STEMI-related shock with prolonged interhospital transport, on observational data.
- Where PCI is not feasible, CABG may be considered.
Temporary Mechanical Circulatory Support
Temporary MCS augments cardiac output, unloads the ventricle and restores perfusion as a bridge to recovery, durable LVAD, transplantation or palliation. Common devices are the intra-aortic balloon pump, the microaxial flow pump and VA-ECMO. (sources/cardiogenic-shock-acc-2025, rating: very high)
Why haemodynamics alone are insufficient. Once multiorgan dysfunction is established, raising cardiac output may not reverse end-organ failure. Three prerequisites must hold for MCS to translate into survival: early timing before MODS is established; adequate restoration of cardiac index; and prevention of device-related complications. MCS should therefore not be last-resort therapy — early initiation limits high-dose catecholamine microvascular toxicity. (sources/mcs-ehj-2014, rating: medium)
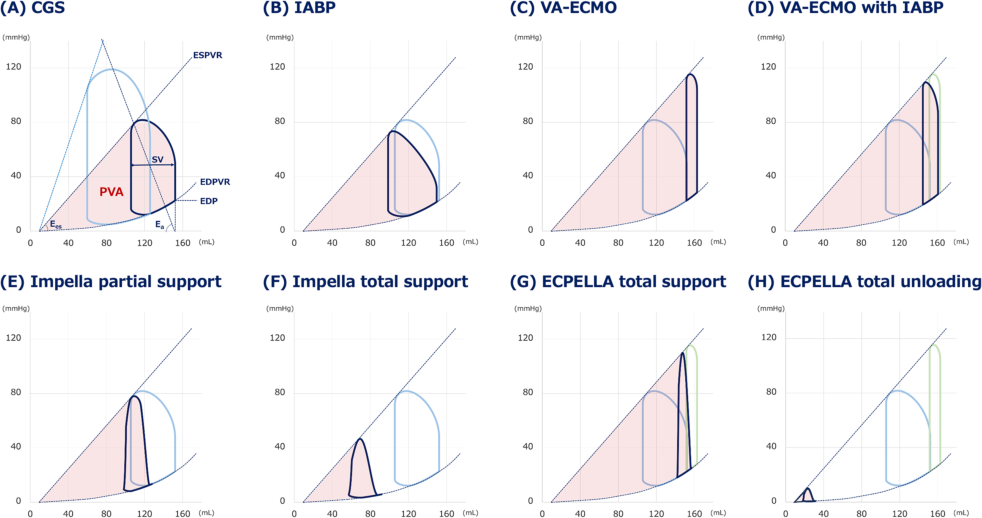
Device haemodynamics on the pressure-volume loop. Pressure-volume area is linearly related to myocardial oxygen consumption: (sources/mcs-jic-2023, rating: high)
- IABP — systolic deflation lowers end-systolic pressure, giving a modest stroke-volume increase and no direct diastolic LV effect; coronary perfusion is augmented by diastolic inflation.
- VA-ECMO — retrograde aortic flow raises LV afterload, shifting the loop rightward and enlarging pressure-volume area, so myocardial oxygen demand rises. Adding IABP gives only limited leftward shift.
- Impella, partial support — the LV still ejects, but end-systolic volume paradoxically rises and pressure-volume area is not sufficiently reduced.
- Impella, total support — LV pressure never reaches aortic pressure, the LV ceases to eject, and pressure-volume area approaches zero: optimal unloading.
- ECPELLA reduces VA-ECMO-induced pressure-volume area while maintaining pressure; excessive decompression risks LV suction, arrhythmia and haemolysis.
Four mechanistic categories organise the percutaneous devices: LV pressure unloading (IABP), LV volume unloading (TandemHeart, Impella), biventricular support without oxygenation, and biventricular support with oxygenation (VA-ECMO). (sources/mcs-ehj-2014)
What the trial evidence shows:
| Trial or analysis | Population | Result |
|---|---|---|
| DanGer Shock (n=360) | STEMI-related shock, selected | Positive — 180-day HR 0.74 (95% CI 0.55–0.99); 12.7% absolute mortality reduction; benefit sustained to 10 years; more bleeding, limb ischaemia and RRT |
| IABP-SHOCK II (n=600) | AMI-related shock | Negative at 30 days and at 6 years |
| ECLS-SHOCK (n=420) | AMI-related shock | Negative — routine early VA-ECMO does not improve outcomes |
| Altshock-2 (n=101) | HF-related shock | Negative — IABP did not improve survival or bridge to replacement at 60 days |
| VA-ECMO 4-trial IPD meta-analysis | AMI-related shock | No mortality benefit; consistently more complications |
| 9-trial IPD meta-analysis (n=1,059) | Mixed | No overall benefit; HR 0.77 (0.61–0.97) only in LV-dominant, low anoxic-brain-injury-risk patients |
(sources/cardiogenic-shock-acc-2025, rating: very high; sources/cardiogenic-shock-nejm-2026)
- Only 5% of all shock patients and 32% of STEMI-related shock patients meet DanGer Shock eligibility, so the result does not generalise to HF-related shock or to AMI-related shock at large.
Device classes in brief. The IABP provides counterpulsation at the lowest support level (~1 L/min increase) with no mortality benefit in either AMI- or HF-related shock and is recommended for mechanical complications in European but not US guidelines; full detail on concepts/IABP. The microaxial flow pump gives continuous LV unloading (CP 4.3 L/min, 5.5 up to 5.5 L/min) and is the only device with a positive RCT, though large propensity-matched series consistently show no benefit with more complications. VA-ECMO gives full cardiopulmonary support up to 6 L/min without unloading the LV. TandemHeart is rarely used. (sources/cardiogenic-shock-nejm-2026)
Routine versus selective use. Routine temporary MCS in all shock patients is strongly discouraged. Selection rests on the cardiac index required, the device's capacity and complication risk, and the haemodynamic profile; a microaxial flow pump may be considered in LV-dominant STEMI-related shock with clinical hypoperfusion. (sources/cardiogenic-shock-acc-2025)
Complication burden scales with device size:
| Device | Bleeding | Limb ischaemia | Stroke |
|---|---|---|---|
| IABP | 12.9% | 1.5% | 3.1% |
| Impella | 27.7% | 4.2% | 4.9% |
| VA-ECMO | 28.2% | 14.3% | 8.2% |
(sources/mcs-jic-2023, rating: high)
Escalation. If support is inadequate for the cardiac index, escalate the device; if unloading is inadequate, increase flow, move to a larger device (CP to 5.5), address afterload by venting the LV on VA-ECMO, or relieve congestion. Delay worsens end-organ perfusion and is lethal.
Right ventricular support and the durable bridge. Impella RP is a percutaneous intracardiac pump from IVC to pulmonary artery, approved under humanitarian device exemption on RECOVER RIGHT; TandemHeart in an RV configuration has case-series data only; CentriMag provides surgical biventricular support up to 10 L/min without RCT evidence. INTERMACS profile 1–2 patients carry 38% 30-day mortality after durable implant, and implants in active shock fell from 40% to 12% between 2006 and 2010 — reflecting recognition that implanting during active shock is prohibitive. A bridge-to-bridge strategy, stabilising on temporary support before durable LVAD, is preferred; 44% of INTERMACS 1–2 durable implants were bridge-to-transplant, and transplant evaluation should run concurrently. (sources/cardiogenic-shock-aha-2017)
Weaning and De-escalation
Assess readiness daily on four axes: haemodynamic stability, total vasoactive drug burden, volume status, and correction of the underlying cause. (sources/cardiogenic-shock-acc-2025, rating: very high)
- Reduce flow stepwise by 0.5–1 L/min every 2–4 hours, evaluating at each step by examination, perfusion metrics, echocardiography and invasive haemodynamics where available.
- Consult advanced HF/transplant before weaning to determine recovery versus durable LVAD versus transplant. Acute-on-chronic HF-related shock may need a prolonged inotrope wean after device removal.
- Structured three-step thresholds: adequate end-organ recovery (improved pressure, normalised lactate, off pressors, improving RA pressure and PAWP) → RV assessment for VA-ECMO decannulation (RA pressure <15 mmHg and PAPi ≥1.0, minimum flow 1.5 L/min) → LV assessment for Impella decannulation (PAWP <20 mmHg and CPO ≥0.6 W, minimum P-level 2).
- Pulse pressure must reappear spontaneously before weaning begins. Significant mitral regurgitation with high PAWP and low CPO should be evaluated for repair before decannulation. (sources/mcs-jic-2023)
Organ Support and the Critical Care Sequence
The care pathway runs Recognise/Rescue → Optimise → Stabilise → De-escalate: identify shock and restore perfusion in the first 24 hours; titrate pharmacological support toward MAP >60–65 mmHg; recover end-organ function and mitigate extracardiac derangement; then assess recovery against durable LVAD, transplant or palliation. (sources/cardiogenic-shock-acc-2025, rating: very high)
- Renal replacement: AKI occurs in 13%–28% and about 20% require RRT during admission. CRRT is preferred over intermittent haemodialysis in haemodynamic instability; the KDIGO Stage 2 threshold governs initiation, and earlier initiation has no outcome benefit. (sources/cardiogenic-shock-aha-2017, rating: high)
- Large-bore access complications: bleeding in up to 60% of AMI-related shock; limb ischaemia is 4× more frequent with temporary MCS and carries 2× the in-hospital mortality. Serial limb and access-site examination, avoidance of excessive anticoagulation and attention to catheter angulation are the preventive measures; uncontrollable bleeding or ischaemia warrants prompt removal, with devices ≥12 Fr removed in the catheter laboratory or operating theatre.
- Ventilation: positive-pressure ventilation reduces LV afterload and augments stroke volume in LV failure; PEEP effects vary with preload dependence, contractility and RV status.
- Palliative care should be engaged early where the patient is not a candidate for durable LVAD, transplant or recovery.
Contradictions / Open Questions
- Device class is not what drives benefit — patient selection is. DanGer Shock is positive (HR 0.74) but only 5% of all shock and 32% of STEMI-related shock patients qualify, while ECLS-SHOCK, IABP-SHOCK II, Altshock-2 and the VA-ECMO IPD meta-analysis are all negative. (sources/cardiogenic-shock-nejm-2026, rating: very high)
- VA-ECMO may harm the LV. Retrograde afterload raises myocardial oxygen demand, and LV venting has been proposed as the remedy — but the transseptal cannula RCT showed no mortality benefit, leaving the optimal unloading strategy unresolved.
- PAC-guided management rests entirely on observational data. No shock-specific RCT exists; PACCS is ongoing; the ESCAPE trial is inapplicable. Practice currently extrapolates. (sources/cardiogenic-shock-acc-2025, rating: very high)
- The optimal MAP target is unresolved. >65 mmHg is standard while a 55 versus 65 mmHg RCT runs; a lower target may reduce afterload but risks organ hypoperfusion.
- Heart-failure-related shock has an evidence void. All positive RCT data come from STEMI-related shock; HF-related management is expert consensus, Altshock-2 was negative, and no positive temporary-MCS RCT exists in that population.
- No vasoactive agent reduces mortality. Cochrane-level evidence establishes equivalence in outcomes for dobutamine and milrinone (DOREMI), an inferior metabolic profile for epinephrine, and more arrhythmia with dopamine — yet practice varies widely between centres.
- Levosimendan failed its dedicated VA-ECMO weaning RCT, while multiple smaller studies and meta-analyses reported benefit; routine use for weaning is unsupported.
- Frailty and device decisions. With 71% of AMI-related shock patients frail, device-related bleeding and limb ischaemia may outweigh any survival benefit — and frailty is not represented in the trials that generated the evidence.
- Stage B intervention is unproven. No randomised evidence supports pre-emptive escalation at Stage B, and DanGer Shock enrolled Stage C/D equivalents, so the "critical intervention window" is an inference from trajectory data rather than a tested strategy.
- Stage E outcomes are highly variable, and the timing of withdrawal of advanced support is a major unresolved question.
- SCAI staging was validated primarily in AMI-related shock; its calibration in HF-related shock is less established.
- Normotensive shock is under-studied relative to hypotensive shock, despite carrying increased mortality.
Connections
- Non-shock decompensation: concepts/Decompensated-HF-Management — decompensated left- and right-sided HF, acute pulmonary oedema
- Device detail: concepts/IABP · concepts/ECPELLA · concepts/Pulmonary-Artery-Pulsatility-Index
- Drug detail: entities/Levosimendan
- Monitoring and physiology: concepts/RHC-Clinical-Applications · concepts/Cardiac-Output-Measurement
- Trial entities: entities/DanGer-Shock-Trial · entities/IABP-SHOCK-II-Trial · entities/ECLS-SHOCK-Trial · entities/DOREMI-Trial · entities/PACCS-Trial · entities/CULPRIT-SHOCK-Trial · entities/Altshock-2-Trial
- Context: entities/Heart-Failure · entities/Acute-Coronary-Syndrome · concepts/ACS-Management · concepts/Cardiorenal-Syndrome
- Right ventricular disease: concepts/Right-Ventricular-Failure