Practical Guidance for Hemodynamic Assessment by Right Heart Catheterization in Management of Heart Failure
Authors, Journal, Affiliations, Type, DOI
- Navin Rajagopalan, Barry A. Borlaug, Alison L. Bailey, Peter M. Eckman, Maya Guglin, Shelley Hall, Matthew Montgomery, Gautam Ramani, Prateeti Khazanie
- JACC: Heart Failure, Vol. 12, No. 7, July 2024, pp. 1141–1156
- Multiple US academic centres (University of Kentucky, Mayo Clinic, Centennial Heart, Alina Health Minneapolis, Indiana University, Baylor, Newark Beth Israel, University of Maryland, University of Colorado-Anschutz)
- State-of-the-Art Review
- DOI: https://doi.org/10.1016/j.jchf.2024.03.020
Overview
This state-of-the-art review provides practical guidance on invasive hemodynamic assessment via right heart catheterization (RHC) for clinicians treating heart failure across the full spectrum — from ambulatory HFpEF and HFrEF to cardiogenic shock, LVAD candidacy, and heart transplantation evaluation. The authors emphasize that RHC is essential when patients have refractory symptoms, volume status is uncertain, or clinical findings are discordant with objective data. Specific clinical scenarios covered include cardiogenic shock staging, HFpEF diagnosis via exercise hemodynamics, pulmonary hypertension phenotyping, LVAD optimization, heart transplantation assessment, portal hypertension differentiation, and high-output HF evaluation.
Keywords
Right heart catheterization; heart failure; hemodynamic assessment; cardiogenic shock; HFpEF; pulmonary hypertension; LVAD; cardiac transplantation; cardiac output; pulmonary capillary wedge pressure
Key Takeaways
Pathophysiology of HF Hemodynamics
- HF is defined by inability to meet circulatory demands without elevated intracardiac pressures; CO reduction is not required for diagnosis
- Elevated central venous pressures → renal venous congestion → worsening renal function; more strongly associated with AKI than low CO
- Elevated PCWP → subclinical lung congestion, impaired exercise capacity, increased HF hospitalization and death
- Neurohormonal/inflammatory pathways from elevated intracardiac pressures → end-organ damage (lungs, kidneys)
- Secondary PH from chronically elevated left-sided filling pressures worsens prognosis regardless of LVEF
- Patients classified into 4 categories by volume status (wet/dry) and CO (warm/cold); clinical exam has limitations particularly in chronic/advanced HF — right-sided pressures may not predict left-sided pressures reliably
RHC Technique and Pitfalls
- Access via internal jugular, femoral, or brachial vein under ultrasound; right IJV preferred (no fluoroscopy needed)
- Transducer zeroed at midthoracic level (level of right atrium); re-zero if data inconsistent
- Pressures measured at end-expiration during normal respiration (functional residual capacity); avoid conscious oversedation (alters breath cycle)
- CO measurement: direct Fick (gold standard, requires direct VO₂ — often unavailable); indirect Fick must be avoided (>25% deviation from true VO₂); thermodilution preferred when direct VO₂ unavailable; thermodilution reasonable even with tricuspid regurgitation; unreliable with intracardiac shunts
- Check SVC and PA oximetry for occult intracardiac shunt on first RHC; PA saturation higher than expected → also consider shunt
- Normal values: RA 0–6 mmHg; RV systolic 20–34/diastolic 0–6 mmHg; PA systolic 20–34/diastolic 8–12/mean ≤20 mmHg; PCWP 4–14 mmHg
- PCWP reported at mid a-wave (or c-wave in AF) at end-expiration for most accurate LV end-diastolic pressure surrogate
- Prominent v-wave: most often reduced LA compliance (stiff LA or LA at steep portion of pressure-volume curve), NOT necessarily significant MR — important distinction in era of catheter-based mitral valve repair; VSD also causes prominent v-wave (consider in recent MI context)
- When v-waves present: report both mean PCWP at mid a-wave AND mean PCWP over entire cardiac cycle; v-wave amplitude influences PVR calculation
- Constrictive pericarditis: RA pressure elevated with accentuated y-descent (> x-descent), positive Kussmaul sign; similar to failing RV (poor prognosis marker)
Cardiogenic Shock
- CS defined as severe myocardial dysfunction → decreased CO + systemic hypoperfusion + tissue ischemia/hemometabolic derangement
- SCAI 2019 updated consensus: 5 CS stages; hemodynamic data + biochemical markers central to classification
- Hypoperfusion (elevated lactate, worsening renal/hepatic function) more ominous than hypotension (normal in early CS)
- Hemodynamic targets in CS: RAP 8–12 mmHg, PCWP ≤15 mmHg, CI ≥2.2 L/min/m²
- CPO = (CO × MAP) / 451; omitting RAP from CPO calculation causes error in CS (RAP frequently elevated); lower prognostic certainty without RAP
- CPO <0.6 W + systemic hypotension despite increasing vasopressor/inotrope support → escalate to temporary MCS
- RV failure hemodynamic markers: RAP >15 mmHg, RAP/PCWP >0.6, PAPI <1.5, RV CPO <0.3 W (where mean PAP replaces MAP)
- HF-CS vs AMI-CS distinction: HF-CS (progressive HF) = more severe hemodynamic derangements but preserved end-organ function + normal serum lactate (chronic adaptation conceals low CO); AMI-CS = abrupt dysfunction → rapid deterioration; easier clinical recognition
- Biventricular CS increasingly recognized; RV sensitive to volume/pressure overload → diuresis to lower RAP + PCWP improves RV mechanics
- Stabilization: vasopressors + inotropes → serial hemodynamic monitoring → vasodilator weaning (if no vasopressors needed) or escalation to temporary MCS → advanced HF therapies (LVAD/transplant) if temporary support fails
- Complex CS decision-making requires HF and surgical specialists; must align with patient goals and values
HFrEF
- Volume overload prevalent in hospitalized HFrEF; RHC not for routine use but useful when volume uncertain or diuretic-refractory
- Clinicians may inappropriately hold diuretics fearing cardiorenal syndrome; RHC demonstrates elevated filling pressures driving renal congestion → justifies diuresis
- Pressure-volume correlation modest — incorporate other volume measures
- Low CO + elevated SVR + maintained perfusion → vasodilatory therapy (ARNI, other oral GDMT; nitroprusside for severe decompensation)
- Low-output HF on GDMT = disease progression → inotropic support (bridge to improvement/LVAD/transplant/palliation); only approved inotropes in US: dobutamine + milrinone (both parenteral)
- Early inotrope studies showed increased mortality → use as bridge only, not indefinite therapy
HFpEF
- HFpEF now more prevalent than HFrEF
- ~1/3 of HFpEF patients have normal PCWP at rest — filling pressures rise exclusively during exercise; physical exam and natriuretic peptides may be normal (particularly with obesity)
- Exercise-induced elevation in PCWP confers 2.4-fold increased risk of HF hospitalization or death
- Gold standard for HFpEF diagnosis: invasive exercise stress test via RHC
- Normal exercise response: mean PAP increase <3.0 mmHg/L/min increase in CO; PCWP <25 mmHg; PVR decreases (vascular distension, recruitment, flow-mediated vasodilation)
- Exercise echocardiography proposed as alternative but inadequate sensitivity to date
- Exercise protocols: escalating workload; simultaneous RAP/PAP/PCWP; CO by direct Fick or thermodilution; metabolic cart; arterial and venous oximetry
- Upright exercise more physiologic but requires specialized equipment; intracardiac pressures lower upright vs supine at rest and during exercise; changes with exercise similar in both positions
- End-expiratory PCWP more strongly correlates with lung congestion than respiratory-averaged PCWP
Pulmonary Hypertension due to HF
- Common in both HFrEF and HFpEF; echocardiography suggests but RHC required to confirm
- World Symposium on PH revised definition: mPAP >20 mmHg (from prior >25 mmHg)
- PH phenotypes determined by PCWP, CO, and PVR:
- Isolated post-capillary PH (IpcPH): elevated PCWP alone
- Combined pre- and post-capillary PH (CpcPH): elevated PCWP + elevated PVR ("out of proportion" to left heart disease)
- CpcPH: more adverse hemodynamic data, greater RV dysfunction, more severe gas exchange impairment, high risk for adverse events — pulmonary arterial vasodilators have not shown benefit in CpcPH
- For normal LVEF + suspected PH: RHC differentiates pre-capillary PH (PAH — elevated mPAP + normal PCWP) from HFpEF (elevated mPAP + elevated PCWP)
- Exercise-induced PH (exaggerated mPAP increase during exercise RHC) is a recognized entity; detailed management beyond scope of paper
LVAD
- Guidelines recommend RHC 1–2 weeks pre-LVAD (elective) or immediately pre-surgery (critically ill) to assess RV dysfunction
- RV failure leading cause of morbidity/mortality post-LVAD
- RV failure risk predictors pre-LVAD: RAP >15 mmHg, RAP/PCWP ratio >0.63, PAPI <1.85 — no single parameter superior; combine with clinical and echo data
- Pre-LVAD hemodynamic optimization: diuretics to achieve RAP <15 mmHg + inotropic support for RV function; RV assist device may be planned simultaneously for severe RV dysfunction
- Post-LVAD hemodynamic targets: RAP <12 mmHg, PCWP <18 mmHg, intermittent aortic valve opening, minimal MR
- LVAD ramp optimization (speed changes during RHC + echo): ISHLT 2023 Guidelines Class IIa; observational data: improves functional capacity, reduces readmissions, lowers LVAD complications
- Late RV failure post-LVAD: increasingly recognized; early signs = fatigue, early satiety, edema, arrhythmias, hepatic/renal dysfunction; requires high index of suspicion; RHC indicated also for myocardial recovery assessment
Heart Transplantation
- 2018 US heart transplant allocation policy: hemodynamic data required for waitlist prioritization
- Indications for inotropic support on waitlist: PCWP >15 mmHg + CI <2.2 L/min/m²
- Indications for escalation to MCS: CI <1.8 L/min/m² (no inotropes) or CI <2.0 (with inotropes) + SBP <90 mmHg
- RHC mandatory pre-transplant to evaluate pulmonary vascular disease
- Relative contraindication: PVR >5 WU or TPG >16 mmHg (risk of donor RV failure)
- Vasodilator challenge indicated when PA systolic >50 mmHg + TPG ≥15 mmHg or PVR ≥3 WU
- Common agents: iNO, prostacyclin, nitroprusside, milrinone, nitroglycerin; nitroprusside ideal if high SVR but may cause hypotension if low MAP
- Favorable response: PVR <3 WU with SBP >85 mmHg → low risk for post-operative RV failure
- Failed acute vasodilator challenge → hospitalization with continuous monitoring + inotropes/diuretics/vasoactive agents → PVR often reduces in 24–48 hours
- If PH remains severe and irreversible: durable LVAD or combined heart/lung transplantation; LVAD support may reduce PVR enabling subsequent heart transplant
- Note: organ shortage + exception requests → higher waitlist prioritization independent of hemodynamics; allocation system under re-evaluation
Portal Hypertension
- HF patients with systemic venous congestion may have liver dysfunction; critical to determine if hepatic cause is portal HTN vs HF-related congestion (portal HTN from liver disease disqualifies from LVAD/transplant)
- Assessment: hepatic vein wedge pressure measurement
- Normal hepatic vein pressure gradient (hepatic vein to hepatic vein wedge): 1–5 mmHg
- Portal hypertension suspected: gradient >5 mmHg
- Elevated hepatic vein pressure + normal gradient → liver abnormalities likely from HF (not intrinsic liver disease)
High-Output HF
- Defined as HF signs/symptoms + CI >4.0 L/min/m²
- Leading causes: obesity, liver disease, arteriovenous fistulas
- AV fistulas → increased venous return/preload, reduced SVR, increased CO → high-output HF, RV failure, PH over time
- Fistula evaluation: measure baseline hemodynamics → repeat after 1-minute fistula compression (shown safe); whether predictive of long-term improvement if fistula modified is unknown
- Fistula takedown/modification → possible cardiac reverse remodeling or improved HF severity in some patients
Data From Embedded Figures and Tables
The source PDF presents its figures as images and its tables as typeset grids. After the 2026-10-16 re-conversion, Tables 1–4 are searchable markdown text in raw/RHC-HF-JACCHF-2024.md (an improvement on the previous conversion, where they were images only), while the figures remain images and are transcribed here with their images embedded. The figure-specific data below — the normal ranges, the 2×2 classification cut-offs, the SCAI criteria in full, and the transplant-allocation thresholds — is stated in the running text only partially or not at all.
Figure 1 — Hemodynamic Classification of Heart Failure Patients
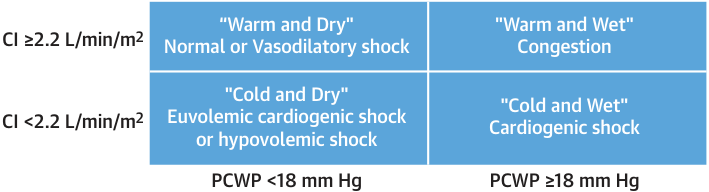
A 2×2 classification on CI 2.2 L/min/m² and PCWP 18 mmHg — the modern cut-offs, not the original Forrester values:
| PCWP < 18 mmHg | PCWP ≥ 18 mmHg | |
|---|---|---|
| CI ≥ 2.2 L/min/m² | "Warm and Dry" — normal or vasodilatory shock | "Warm and Wet" — congestion |
| CI < 2.2 L/min/m² | "Cold and Dry" — euvolemic cardiogenic shock or hypovolemic shock | "Cold and Wet" — cardiogenic shock |
Figure 2 — Basics of RHC Hemodynamics: Normal Ranges
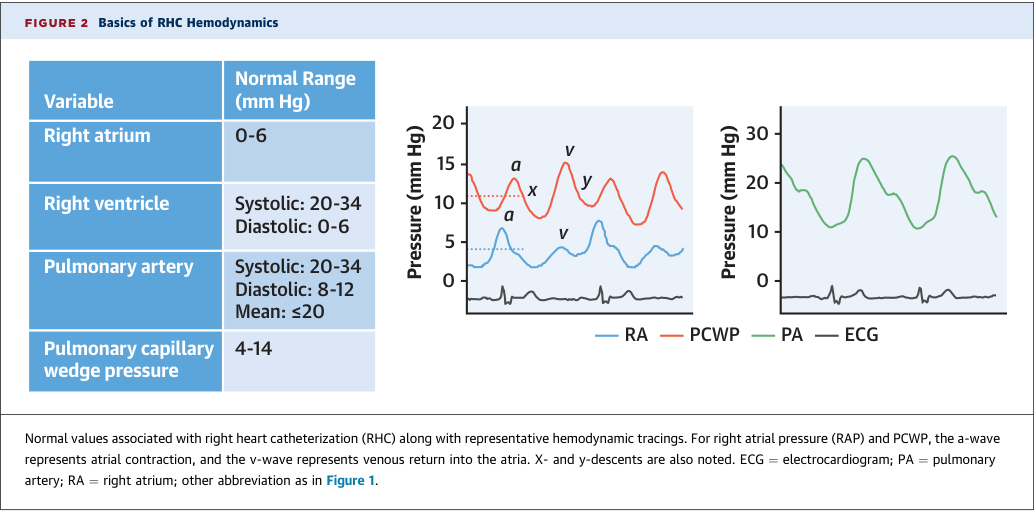
| Variable | Normal range (mmHg) |
|---|---|
| Right atrium | 0–6 |
| Right ventricle | Systolic 20–34; Diastolic 0–6 |
| Pulmonary artery | Systolic 20–34; Diastolic 8–12; Mean ≤ 20 |
| Pulmonary capillary wedge pressure | 4–14 |
- The figure also shows representative tracings labelling the a-wave (atrial contraction), v-wave (venous return into the atria), and the x- and y-descents, for both RA pressure and PCWP
Figure 3 — Examples of Hemodynamic Tracings
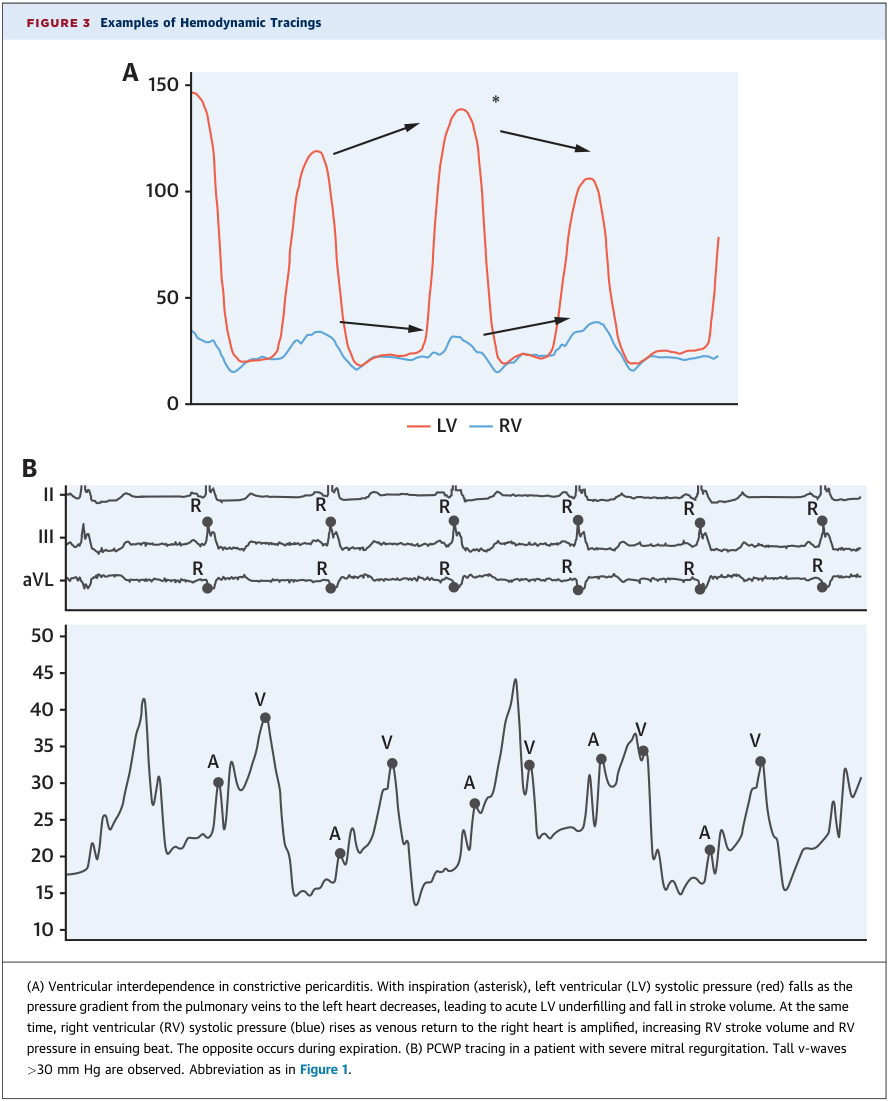
| Panel | Finding | Interpretation |
|---|---|---|
| A | Simultaneous LV and RV pressure traces, constrictive pericarditis | With inspiration, LV systolic pressure falls (the gradient from pulmonary veins to LV decreases → acute LV underfilling and reduced stroke volume) while RV systolic pressure rises (amplified venous return → increased RV stroke volume). The opposite occurs during expiration. A respiratory variation of >30 mmHg is observed |
| B | PCWP trace with simultaneous ECG (II, III, aVL) | Severe mitral regurgitation — tall v-waves in the PCWP tracing |
- This is the tracing evidence for the two commonest interpretive errors: respiratory variation (panel A) and v-wave inflation of the mean (panel B). Both mandate reading at end-expiration and, where large v-waves are present, reporting the mean PCWP
Figure 4 — Cardiogenic Shock Classification (SCAI Stages A–E)
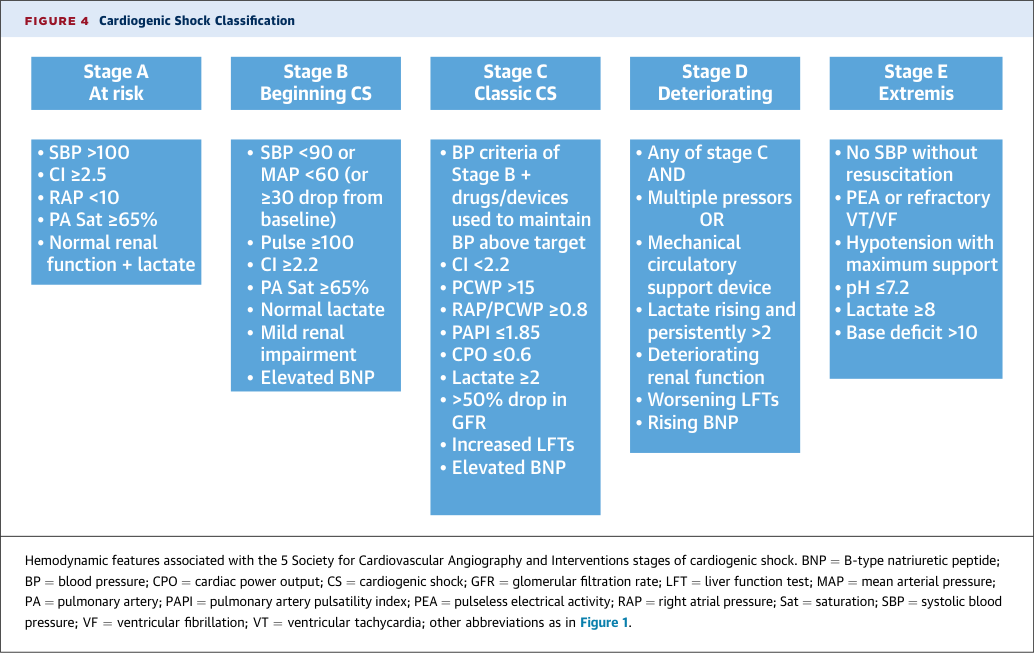
The full haemodynamic and biochemical criteria for each SCAI stage. Note that the running text states these criteria only in part; the re-converted markdown carries them but with the columns interleaved, so the image remains the readable source.
| Stage | Criteria |
|---|---|
| A — At risk | SBP > 100; CI ≥ 2.5; RAP < 10; PA saturation ≥ 65%; normal renal function and lactate |
| B — Beginning CS | SBP < 90 or MAP < 60 (or ≥ 30 drop from baseline); pulse ≥ 100; CI ≥ 2.2; PA sat ≥ 65%; normal lactate; mild renal impairment; elevated BNP |
| C — Classic CS | BP criteria of Stage B plus drugs/devices to maintain BP above target; CI < 2.2; PCWP > 15; RAP/PCWP ≥ 0.8; PAPI ≤ 1.85; CPO ≤ 0.6; lactate ≥ 2; > 50% drop in GFR; increased LFTs; elevated BNP |
| D — Deteriorating | Any of Stage C AND multiple pressors OR a mechanical circulatory support device; lactate rising and persistently > 2; deteriorating renal function; worsening LFTs; rising BNP |
| E — Extremis | No SBP without resuscitation; PEA or refractory VT/VF; hypotension with maximum support; pH ≤ 7.2; lactate ≥ 8; base deficit > 10 |
Figure 5 — Diagnosis of Pulmonary Hypertension
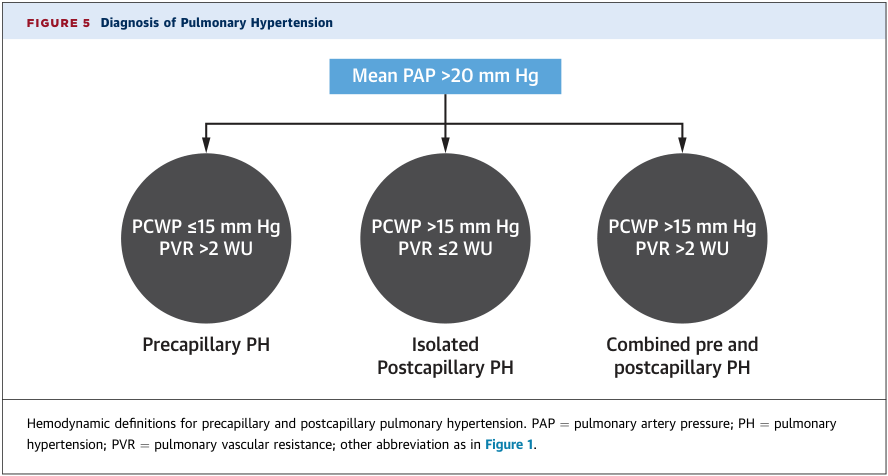
Starting from mean PAP > 20 mmHg, the three phenotypes separate on PCWP and PVR:
| Phenotype | PCWP | PVR |
|---|---|---|
| Precapillary PH | ≤ 15 mmHg | > 2 WU |
| Isolated postcapillary PH | > 15 mmHg | ≤ 2 WU |
| Combined pre- and postcapillary PH | > 15 mmHg | > 2 WU |
Figure 6 — Assessment of Portal Hypertension
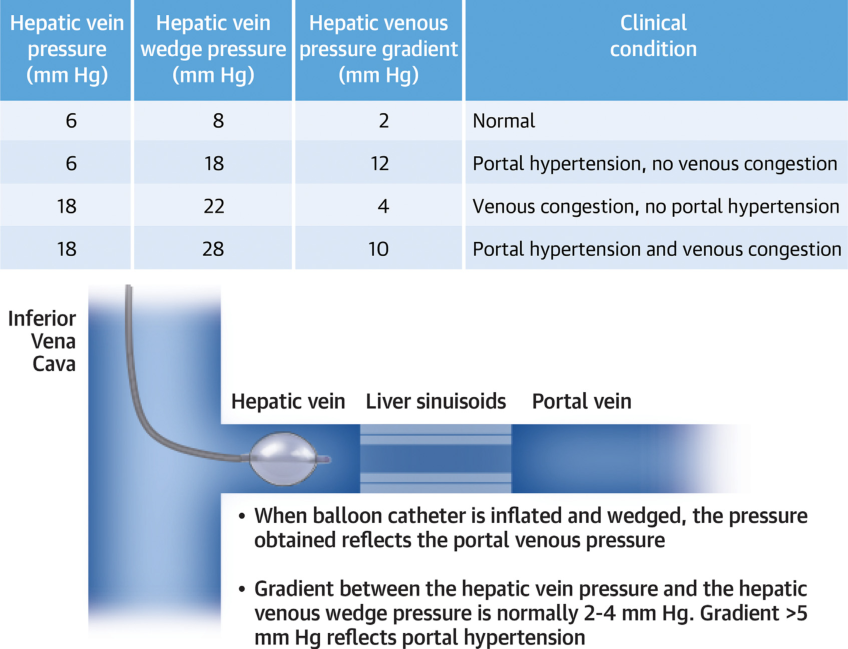
A balloon catheter is advanced to wedge in a hepatic vein; when inflated, the pressure obtained reflects portal venous pressure, and the clinical state is read from the gradient:
| Hepatic vein pressure | Hepatic vein wedge pressure | Gradient | Clinical condition |
|---|---|---|---|
| 6 | 8 | 2 | Normal |
| 6 | 18 | 12 | Portal hypertension, no venous congestion |
| 18 | 22 | 4 | Venous congestion, no portal hypertension |
| 18 | 28 | 10 | Portal hypertension and venous congestion |
- The gradient between hepatic vein pressure and hepatic venous wedge pressure is normally 2–4 mmHg; a gradient > 5 mmHg reflects portal hypertension. The four rows are the worked examples that distinguish congestion from portal hypertension when both pressures are elevated
Central Illustration — Use of Right Heart Catheterization in Heart Failure
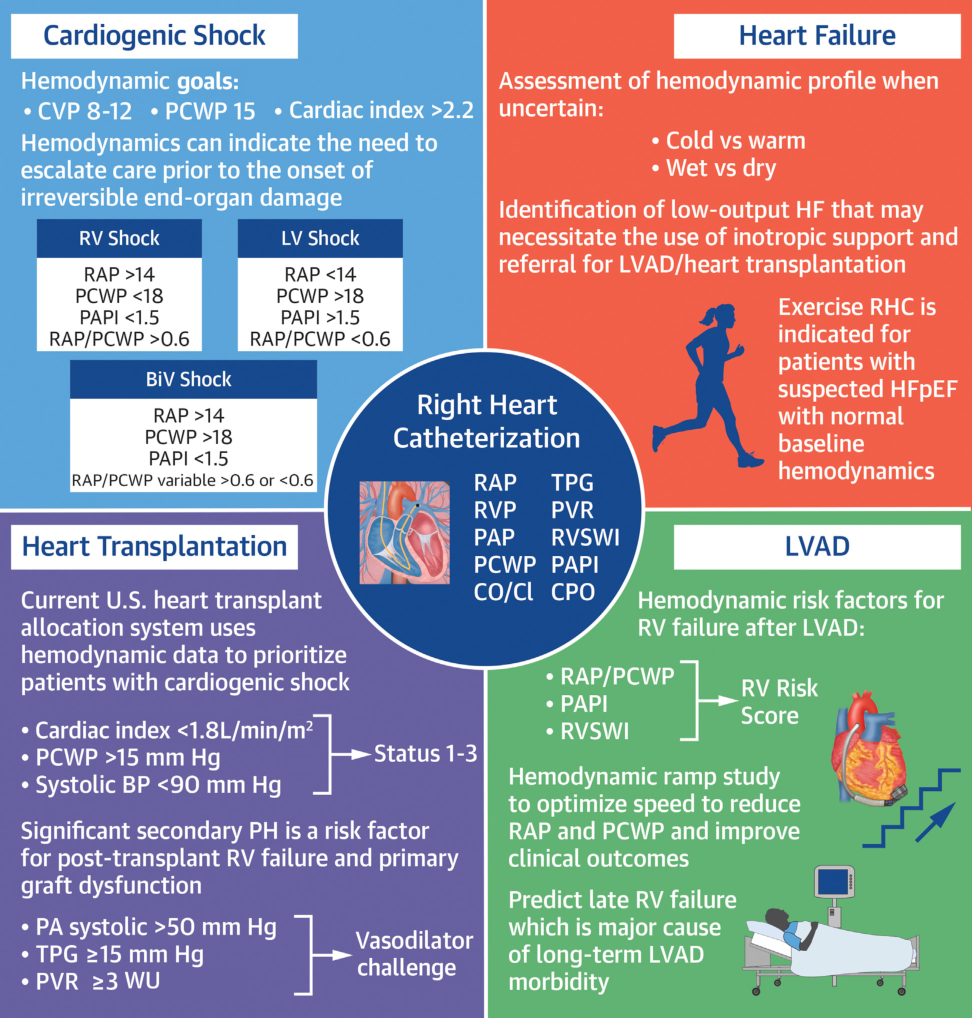
The paper's summary figure, carrying four distinct threshold sets:
- Cardiogenic shock — haemodynamic goals: CVP 8–12, PCWP 15, cardiac index > 2.2. Haemodynamics can indicate the need to escalate care before irreversible end-organ damage
- RV shock: RAP > 14, PCWP < 18, PAPI < 1.5, RAP/PCWP > 0.6
- LV shock: RAP < 14, PCWP > 18, PAPI > 1.5, RAP/PCWP < 0.6
- BiV shock: RAP > 14, PCWP > 18, PAPI < 1.5, RAP/PCWP variable (> 0.6 or < 0.6)
- Heart failure — assess the haemodynamic profile when uncertain: cold vs warm, wet vs dry; identify low-output HF that may need inotropic support and referral for LVAD/transplantation. Exercise RHC is indicated for patients with suspected HFpEF and normal baseline haemodynamics
- Heart transplantation — the current U.S. allocation system uses haemodynamic data to prioritise patients with cardiogenic shock: CI < 1.8 L/min/m², PCWP > 15 mmHg, systolic BP < 90 mmHg → Status 1–3. Significant secondary PH is a risk factor for post-transplant RV failure and primary graft dysfunction: PA systolic > 50 mmHg, TPG ≥ 15 mmHg, PVR ≥ 3 WU → vasodilator challenge
- LVAD — haemodynamic risk factors for RV failure after LVAD: RAP/PCWP, PAPI, RVSWI → RV Risk Score. A haemodynamic ramp study optimises speed to lower RAP and PCWP. Late RV failure is a major cause of long-term LVAD morbidity
- Core measured variables: RAP, RVP, PAP, PCWP, CO/CI, plus the derived TPG, PVR, RVSWI, PAPI and CPO
Tables 1–4 (now text in the markdown)
- Table 1 — Common clinical occurrences during RHC: a mechanism/troubleshooting grid for improper zeroing, overdamping, catheter whip, under-wedged and over-wedged PCWP tracing, significant respiratory variation, MR with tall v-waves, and inaccurate CO by thermodilution and by Fick. Note that over-wedging "can cause pulmonary artery rupture" and is characterised by loss of a- and v-waves with loss of respiratory variation
- Table 2 — Calculations to obtain during RHC: every derived variable with its formula and normal range — TPG = mean PAP − PCWP (< 12); PVR = TPG/CO (< 2); SVR = (MAP − RAP)/CO × 80 (900–1,200 dyne·s/cm⁵); PAPI = (PA systolic − PA diastolic)/RAP (> 2.0); RVSWI = (mean PAP − RAP) × (CI/HR × 1,000) × 0.0136 (> 8 g·m/m²/beat); CPO = (MAP − RAP) × CO / 451 (> 1.0 W)
- Table 3 — Clinical criteria suggesting the need for RHC in chronic HFrEF
- Table 4 — Use of RHC in patients with durable LVAD: Class I for recurrent HF symptoms (RV failure, device malfunction, inadequate LV unloading) and for heart transplantation evaluation (assess TPG and PVR; reversibility testing if PVR > 3 WUs; serial testing if extended wait-time); Class IIa for ramp study and for myocardial recovery assessment. Based on the 2023 ISHLT MCS guidelines
Limitations of the document
- Narrative state-of-the-art review (not systematic review or meta-analysis); evidence quality not formally graded
- Many recommendations based on observational data and expert consensus; no CS-specific RCT for RHC (PACCS ongoing)
- RCT benefit data for RHC in HF hospitalization/survival gaps acknowledged
- Most exercise hemodynamic protocols from tertiary/specialized centres; not widely generalizable
- Heart transplant allocation analysis limited to US system (2018 policy)
- Figures survive only as images. All six figures and the Central Illustration are graphics with no selectable text in the PDF, so their content is not searchable in
raw/RHC-HF-JACCHF-2024.md. All have been read and transcribed into Data From Embedded Figures and Tables above — but that transcription is manual, and carries a manual-transcription error risk. Figure 4's criteria are the worst affected: the re-converted markdown contains them, but with the SCAI stage columns interleaved into an unreadable jumble, so the image is the only legible source for that figure - 72 replacement characters (
�) remain in the raw markdown, mostly as list-bullet glyphs inside the re-converted tables. They are cosmetic and do not obscure the data, but they will appear in any verbatim quotation from those tables
Key Concepts Mentioned
- concepts/Right-Heart-Catheterization — primary topic; pitfalls, normal values, clinical applications
- concepts/Cardiogenic-Shock — CS staging, hemodynamic targets, CPO use
- concepts/Pulmonary-Hypertension — PH phenotyping (IpcPH vs CpcPH), PA vasodilators in HF-PH
- concepts/Pulmonary-Artery-Pulsatility-Index — LVAD and CS thresholds
- concepts/Cardiopulmonary-Exercise-Testing — invasive exercise hemodynamics in HFpEF
Key Entities Mentioned
- entities/HFpEF — 1/3 normal resting PCWP; exercise RHC gold standard
- entities/HFrEF — RHC for cardiorenal syndrome, inotrope use
- entities/LVAD — pre/post RHC protocol, ramp optimization
- entities/Heart-Transplantation — mandatory RHC, vasodilator challenge, allocation criteria
Wiki Pages Updated
2026-10-16 — re-converted, one figure re-attached, all figures transcribed:
raw/RHC-HF-JACCHF-2024.md— re-converted with the pinnedpymupdf4llmengine: headings 2 → 19, table rows 6 → 34, lines 3,387 → 648,meta.jsoncreated (16 pages, sha3753cf3917ad8ccc). Fixed by the re-conversion: 364 split-word fragments (hemody/namic,trans/plantation), letter-spaced headers (J A C C : H E A R T F A I L U R E), and publisher XML artifacts ((Delta:1_given name)/(Delta:1_surname)leaked from Elsevier markup)wiki/sources/rhc-hf-jacchf-2024.md— new Data From Embedded Figures and Tables section; Figure 4's image re-attachedwiki/concepts/Right-Heart-Catheterization.md— normal haemodynamic ranges addedwiki/sourceindex.md,wiki/wikiindex.md— rows refreshed
Why the re-conversion was kept. The preview initially looked like a loss — 14 images down to 7 — but the figures were checked individually and the loss was one figure, not seven: Tables 1–4 became searchable text tables (an improvement), and old images 8-0/8-1 were two renderings of the same Central Illustration. Figure 4 (7-0, the SCAI classification) was genuinely dropped and has been re-inserted at its caption. Token count was 10,188 → 10,173 across the conversion, with 364 of the 390 backup-only words being split-word fragments.
wiki/sources/rhc-hf-jacchf-2024.md— created (this file)wiki/concepts/Right-Heart-Catheterization.md— added HF-CS vs AMI-CS distinction, portal hypertension assessment, high-output HF, HFpEF exercise statistics, SCAI targets; source_count updatedwiki/concepts/Invasive-Hemodynamic-Monitoring-CS.md— added HF-CS vs AMI-CS distinction; source updatedwiki/sourceindex.md— new entry addedwiki/wikiindex.md— RHC entry description updated